Most guides to gastroenterology marketing start with search ads and end with review widgets, as if a GI practice were a med spa with a colonoscope. It isn’t. A large share of a gastroenterology practice’s new patients never searched for a gastroenterologist at all. Their primary care physician saw an abnormal stool test, a hospitalist discharged them with a follow-up order, or an urgent care clinician told them the bleeding needed a specialist this week. The patient asked one question, which was who, and the answer came from another doctor.
That single fact should reorganize how a GI practice thinks about growth. Gastroenterology marketing is not one system but three: a referral system for the patients who are sent, a recall system for the patients the practice already has, and a direct system for the patients who search. Most practices run only the third, and run it badly, while the first two go unmanaged. The practices filling their procedure schedules consistently are the ones that built all three and understood which one carries the most weight. That starts with treating physician referral marketing as the primary channel it actually is, rather than a relationship that happens on its own.
| Where GI patient volume comes from | What actually drives it | What most practices do instead |
|---|---|---|
| Physician referrals | Fast consult notes, easy intake, a direct line for urgent patients, closed loops back to the referrer | Assume the relationship maintains itself |
| Screening recall | Systematic outreach to patients who are due, overdue, or had a positive stool test with no follow-up | Wait for the patient or the PCP to remember |
| Direct patient search | Condition and procedure pages in patient language, a current Business Profile, reviews that mention the things anxious patients read for | One “Services” page and a profile last touched at opening |
| Prep completion | Clear, staged instructions delivered the way patients actually read them | A printed sheet handed over at scheduling |
The referral side comes first because it is the largest channel and the worst tended. A primary care physician with a patient who needs a gastroenterologist is not comparing websites. They are reaching for whichever name is easiest to reach for, and that usually means the practice that last made their job easier. A GI practice that returns a consult note within days, accepts the referral without making the sending office chase a fax confirmation, offers a protected way to get an urgent patient seen quickly, and closes the loop so the referrer knows what happened becomes the default answer to the question who. The alternative has no floor. A practice that does none of those things is a name on a list, and lists get shuffled.
What makes this a marketing discipline rather than an operations one is that the referrer has to know the practice exists and be able to describe it in a sentence. Most GI practices cannot say in a sentence what distinguishes them: which procedures they perform in-office versus at the hospital, what the wait is for a new consult, whether they handle anesthesia-assisted endoscopy, which plans they take. A referral coordinator with a one-page summary of exactly those facts, delivered in person to the offices that send the most patients and updated the week anything changes, does more for procedure volume than any ad campaign the practice could buy. The sending physician does not want a brochure. They want the wait time, the procedure list, and the phone line that gets a scared patient seen, stated plainly enough to repeat in the exam room.

The second system is the one almost nobody runs, and it is the closest thing gastroenterology has to a demand channel the practice controls outright. The U.S. Preventive Services Task Force recommends colorectal cancer screening beginning at age 45, having lowered the starting age from 50 in its most recent recommendation. That change expanded the eligible population, and every year a new cohort crosses into it. The Task Force’s own figures make the gap plain: at the time of the recommendation, roughly a quarter of eligible adults had never been screened, and nearly a third were not up to date. Those people are not a marketing audience in the usual sense. Many of them are already patients of the practice, or patients of a primary care office that already refers to it, and they simply have not been asked.
Screening recall is the practice of asking. It means identifying every patient in the system who is due or overdue, every patient whose last colonoscopy is approaching its interval, and every patient who had a positive at-home stool test and never completed the follow-up colonoscopy that a positive result requires. Then it means reaching them, in the order that matters, with a message that makes scheduling easy. Practices that build this as a standing process rather than an occasional campaign generate procedure volume from patients they already have, at a cost that no paid channel can match. The measure of whether it is working is the same one that governs every other channel: patient acquisition cost per booked procedure, and recall is almost always the lowest number on the board.
The follow-up population deserves its own line because it is both the highest-value and the most neglected. A patient whose at-home stool test comes back positive needs a colonoscopy regardless of why they chose the at-home test in the first place. Many of them do not know that, or know it and put it off. A practice that tracks positive results from the referring offices it works with, and reaches out to those patients directly with a clear explanation of the next step, is doing exactly the work a referral relationship is supposed to enable. It is also doing something the referring physician will notice and remember.
The third system is the one everyone builds, usually before the other two, and it behaves like search in any other specialty with a few gastroenterology wrinkles. A patient with a new diagnosis, a family history, a symptom they have been ignoring for months, or a recommendation to get a second opinion goes to a search box. They do not type “gastroenterologist.” They type the symptom, the procedure, or the test: heartburn that will not stop, blood in stool, what a colonoscopy involves, how long a capsule endoscopy takes. The practice that appears for those searches and has a page that speaks to that specific situation wins the visit. The practice with a single services page and a Business Profile last updated at opening wins nothing.

That means the website has to be built around procedure and condition pages, one per topic, written in the words a patient uses rather than the words a chart records. A page for colonoscopy that explains what the visit involves, what the prep is like, and what happens if a polyp is found. A page for upper endoscopy. A page for reflux, for irritable bowel, for inflammatory bowel disease, for hemorrhoids, for celiac evaluation. Each one answering the four questions every anxious searcher carries: do you treat what I have, can I trust you, how close are you, and how soon can I be seen. The insurance list belongs on the page as text, never as a downloadable file. Coverage doubt is one of the two questions that stops a nervous patient from calling, and a PDF will not get opened. Purpose-built medical website design for a GI practice is mostly the discipline of building those pages and connecting them to a booking path that works on a phone.
Reviews matter more in gastroenterology than in most specialties because the reader is often embarrassed as well as worried. A patient researching a colonoscopy or a rectal bleeding workup is reading for signs that the practice will treat them with dignity, explain things plainly, and not make the experience worse than it has to be. The reviews that reassure are specific: a procedure that went smoothly, staff who handled an awkward question gracefully, a physician who explained a result in plain language. A practice’s review-request habit should aim at exactly those moments.
There is a newer layer on top of the direct system. Patients increasingly get their first answer from an AI-generated summary rather than a list of links, and the practices that get cited there are the ones with clearly structured pages and plainly written answers to common questions. Building for AI-driven search visibility is now part of what a gastroenterology practice’s content has to do, and the same procedure pages that rank in traditional results are the ones most likely to be cited in a generated answer.
The fourth thing is not a channel at all, which is exactly why it gets left out of gastroenterology marketing plans. It is prep. A scheduled colonoscopy that the patient does not prepare for correctly becomes a cancellation, a reschedule, or an incomplete exam that has to be repeated. Every one of those outcomes costs the practice a procedure slot it had already filled, and most of them trace back to a communication failure rather than a clinical one. The patient got a printed sheet at scheduling, put it somewhere, and started the prep late or wrong.

Prep instructions are marketing operations in disguise. The practices with the fewest prep-related losses deliver instructions in stages, timed to when the patient needs each one, through the channel the patient actually reads. A message a week out about what to buy and what to stop taking. A message two days out about the diet change. A message the evening before walking through the split-dose timing. A message the morning of confirming the arrival time and the ride home. The National Institute of Diabetes and Digestive and Kidney Diseases publishes patient-facing guidance on what colonoscopy preparation involves, and a practice’s own sequence should be built around the same plain-language principles. When a patient does cancel, the practice needs a clear, consistently applied appointment cancellation policy so the slot can be refilled from a waitlist rather than lost. None of this is expensive. It is a small fraction of what the practice spends acquiring the patient in the first place, and it protects the revenue that was already on the schedule.
The same staged-communication logic applies to the chronic population. Patients managing inflammatory bowel disease or a long-running functional condition return for flare management, medication adjustments, and surveillance scoping over years. Marketing for this segment is not about the first visit. It is about staying present between visits, so the practice remains the patient’s clinical home rather than a place they went once. Consistent, useful outreach between appointments, written for patients rather than at them, is the substance of good healthcare content marketing in a specialty where the relationship is measured in years.
Once the three systems and the prep layer are understood, the budget conversation becomes simpler than most practice owners expect. The referral system costs staff time and discipline more than money. The recall system costs a list, a process, and a message sequence. The direct system costs a one-time investment in the profile, the procedure pages, and the review process, followed by maintenance. Prep communication costs a set of templates and a schedule. Paid search belongs last, and it belongs only on the direct side, for specific procedure searches where the practice already has a page worth sending a patient to. The common failure inverts the order: a practice buys ads before building the systems underneath them, pays to send anxious patients to a page that does not answer their question, and concludes that marketing does not work in gastroenterology. It works. It simply looks different from the marketing that wins in specialties where the patient chooses alone.
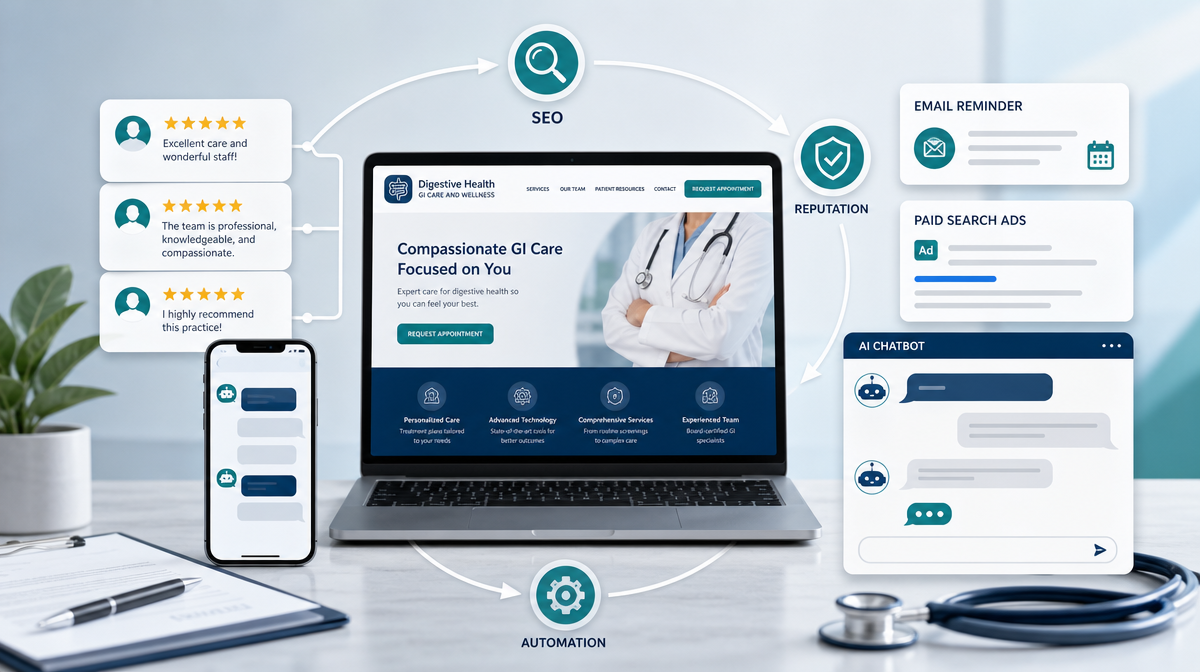
Running all of it as one connected program is where the compounding happens. Referral volume by sending office, recall completions, procedure-page visits, review velocity, and prep-related cancellations belong on the same dashboard, because a movement in any one of them usually explains a movement in another.
A.L.I. 360 by Target Patients MD is a proprietary AI-powered patient-acquisition system for medical and dental practices. The name stands for Attract, Learn, and Influence. For a gastroenterology practice, that means the referral, recall, and direct systems are measured together, and the prep and follow-up messaging runs on the same platform that tracks whether the schedule is actually filling.
Gastroenterology marketing belongs to the practice that is easiest to refer to, most diligent about the patients it already has, and easiest to find at the moment a worried person finally searches. All three are things a practice can build deliberately, in a defined order, without spending much on advertising at all. The referral side fills the schedule, the recall side turns the existing patient base into a standing source of procedures, the search side captures the self-directed, and the prep layer makes sure booked appointments actually happen. The playbook is not the one that works for the med spa down the street. The practices growing fastest stopped borrowing it.
Practice owners exploring gastroenterology marketing tend to ask the same handful of questions before committing to a strategy. Here are direct answers to the ones that come up most often.
- What is gastroenterology marketing?
It is the coordinated work of growing a GI practice through three connected systems: physician referral relationships, screening recall for existing patients, and direct search visibility for patients researching symptoms and procedures. It also includes the communication work that keeps booked procedures from turning into cancellations, which is where most GI practices lose volume they had already won. - How do gastroenterology practices get more referrals?
By making themselves the easiest practice to refer to. That means fast consult notes, referral intake that does not require the sending office to chase confirmations, a protected way to get urgent patients seen quickly, and a one-page summary of wait times, procedures, and accepted plans delivered in person to the offices that send the most patients and updated whenever anything changes. - How can a GI practice reduce colonoscopy no-shows?
Most prep-related cancellations are communication failures, not clinical ones. Delivering prep instructions in stages, timed to when the patient needs each step and sent through the channel they actually read, reduces late or incorrect prep. A clear cancellation policy paired with an active waitlist lets the practice refill slots that do open up. - What should be on a gastroenterology practice website?
One page per procedure and condition, written in the words patients use rather than chart terminology, each answering whether the practice treats their problem, why they should trust it, where it is, and how soon they can be seen. Insurance information should appear as text on the page, and the booking path should work on a phone without pinching or zooming. - How long does it take to see results from gastroenterology marketing?
Referral and recall improvements can show up in the schedule within weeks, because they draw on relationships and patients the practice already has. Search visibility builds more gradually, with procedure pages taking months to establish position, which is why the referral and recall systems should be built first and the direct system layered on top of them.